
Learning Objectives
- Detail the pathophysiology and neuroanatomical mechanisms of syringomyelia, identifying the formation of a fluid-filled, gliosis-lined cavity (syrinx) within the cervical to upper thoracic cord (C2–T9).
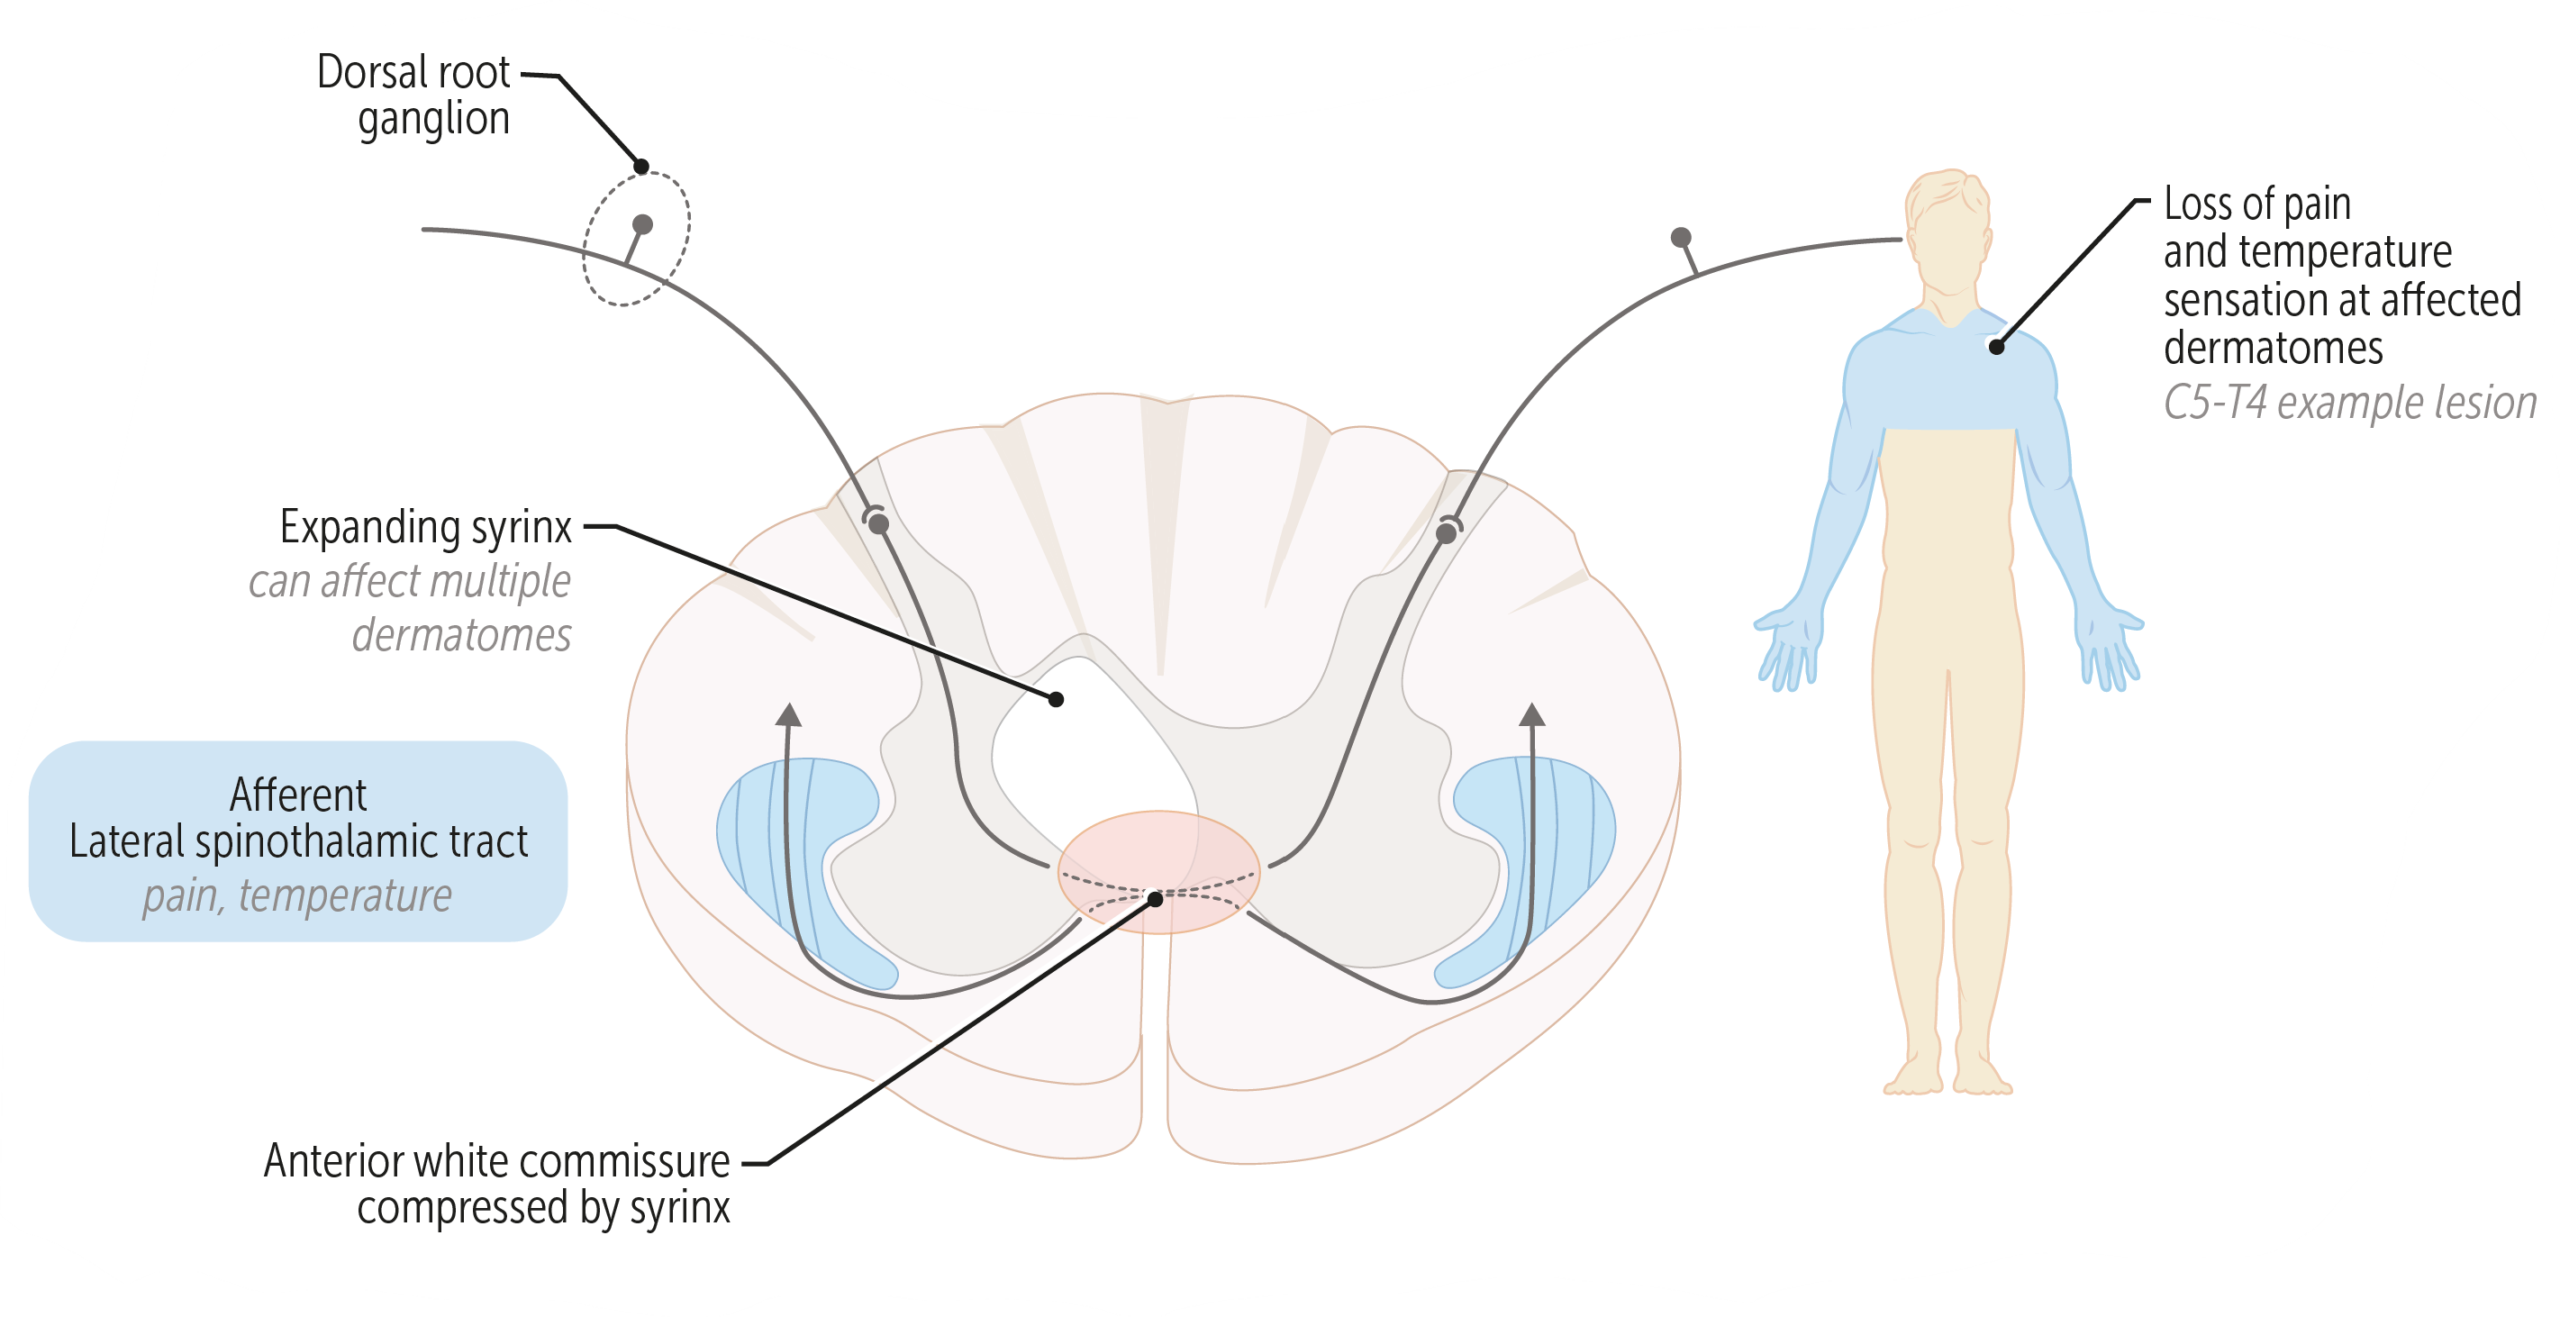
- Explain the selective damage to the anterior white commissure and its disruption of crossing fibers of the spinothalamic tract.
- Correlate physical examination findings with lesion progression, recognizing the classic bilateral “cape-like” loss of pain and temperature sensation while touch and vibration remain preserved.
- Recognize lower motor neuron (LMN) weakness and upper limb atrophy resulting from anterior horn involvement, and identify its frequent association with Chiari I malformation.
1. Syringomyelia Pathophysiology & Clinical Features
A cystic cavitation within the spinal cord parenchyma selectively interrupts decussating sensory pathways and anterior horn motor neurons, producing a distinctive neurological syndrome.
| Clinical Feature | Anatomical Mechanism | Symptom Description |
|---|---|---|
| Loss of Pain & Temperature | Compression of crossing fibers in the anterior white commissure (spinothalamic tract). | Bilateral “cape-like” distribution over the shoulders, arms, and upper trunk. |
| Preserved Touch & Vibration | The dorsal columns (posterior columns) are located superficially and remain uninjured. | Intact fine touch, proprioception, and vibratory sense. |
| Upper Limb LMN Weakness | Expansion of the syrinx laterally into the anterior horns of the grey matter. | Flaccid paralysis, muscle atrophy, areflexia, and fasciculations in the hands and forearms. |
| Associated Pathology | Impaired CSF dynamics at the foramen magnum. | Most commonly linked to Chiari I malformation (cerebellar tonsillar herniation). |
Clinical Notes & Pathology:
- Dissociated Sensory Loss: The selective loss of pain and temperature while fine touch and position sense are spared is the hallmark diagnostic clue for central cord cavitation.
- Burn and Injury Vulnerability: Because patients cannot feel thermal or painful stimuli on their upper extremities, they frequently suffer painless burns or cuts on their hands without realizing it.
- Extension to Horner’s Syndrome: If the syrinx expands laterally to involve the intermediolateral cell column (ciliospinal center of Budge at T1–T2), it can cause ipsilateral Horner syndrome (ptosis, miosis, anhidrosis).
Key Points & Memory Hooks:
Cape-Like Distribution: Picture a cape draped over the shoulders and upper back—this is the exact zone where spinothalamic crossing fibers are destroyed.
Anterior White Commissure Target: The syrinx expands from the central canal outward, hitting the crossing pain fibers first.
Chiari I Link: Always associate adult-onset cervical syringomyelia with tonsillar herniation obstructing normal CSF flow out of the fourth ventricle.
Cape-Like Distribution: Picture a cape draped over the shoulders and upper back—this is the exact zone where spinothalamic crossing fibers are destroyed.
Anterior White Commissure Target: The syrinx expands from the central canal outward, hitting the crossing pain fibers first.
Chiari I Link: Always associate adult-onset cervical syringomyelia with tonsillar herniation obstructing normal CSF flow out of the fourth ventricle.
You must be logged in to post a comment.