
Learning Objectives
- Master the stages of heart morphogenesis, cardiac looping, and left-right axis determination.
- Trace the detailed sequence of atrial septation, ventricular septation, and aorticopulmonary outflow tract formation.
- Recognize high-yield congenital anomalies including patent foramen ovale, VSD, AVSD, and neural crest conotruncal defects.
Heart Morphogenesis & Cardiac Looping
| Developmental Step | Morphological Process & Timing | Clinical Correlation & Pathology |
|---|---|---|
| Heart Morphogenesis | First functional organ in vertebrate embryos; begins beating spontaneously by week 4 of development. | Early embryonic failure results in major structural or lethal anomalies. |
| Cardiac Looping | Primary heart tube loops to establish left-right polarity; begins in week 4 of development. | Defects in left-right dynein lead to dextrocardia (e.g., Kartagener syndrome / primary ciliary dyskinesia). |
Septation of the Atria
| Step | Atrial Septation Mechanism | Anatomical Landmark |
|---|---|---|
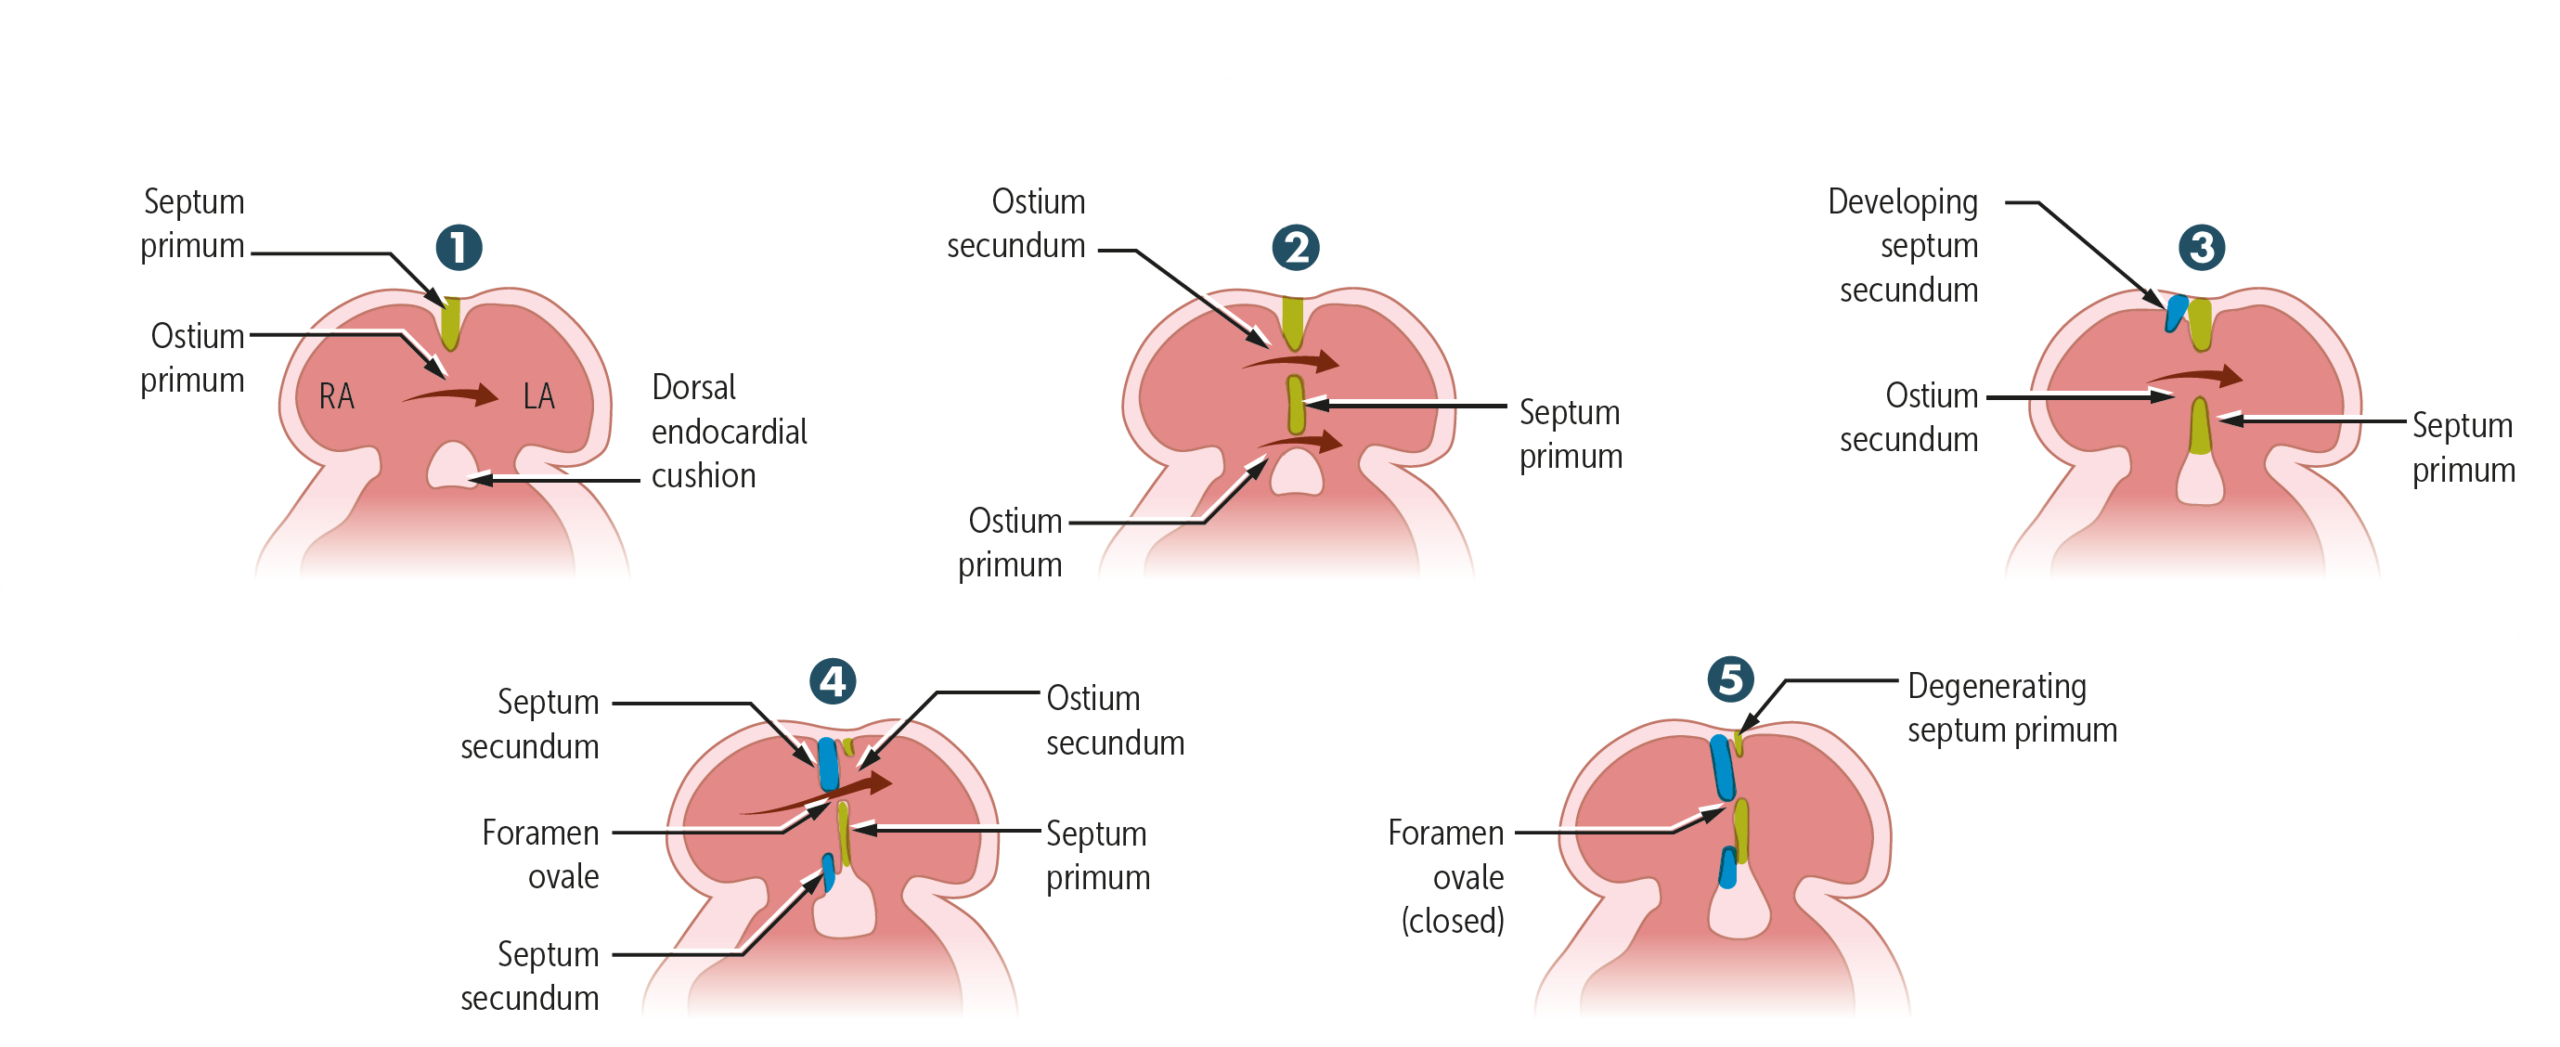
| 1 | Septum primum grows toward endocardial cushions, narrowing the ostium primum. | Ostium primum |
| 2 | Ostium secundum forms in septum primum via cell death as ostium primum regresses. | Ostium secundum |
| 3 & 4 | Septum secundum develops on the right side, expanding to cover most of ostium secundum, leaving the foramen ovale. Remaining septum primum forms the one-way valve. | Foramen ovale |
| 5 & 6 | At birth, $\uparrow$ left atrial (LA) pressure and $\downarrow$ right atrial (RA) pressure push septum primum against septum secundum, sealing the foramen ovale. | Functional closure at birth |
| 7 | Septum secundum and septum primum fuse during infancy/early childhood to form the permanent atrial septum. | Anatomical fusion |
Atrial Septal Anomalies:
- Patent Foramen Ovale (PFO): Failure of septum primum and secundum to fuse after birth (present in ~25% of population). Most are asymptomatic.
- Clinical Risk: Can lead to paradoxical emboli (venous thromboemboli crossing from right to left into systemic circulation).
Septation of the Ventricles & Endocardial Cushions
| Structure / Process | Formation & Embryological Origin | Associated Pathology |
|---|---|---|
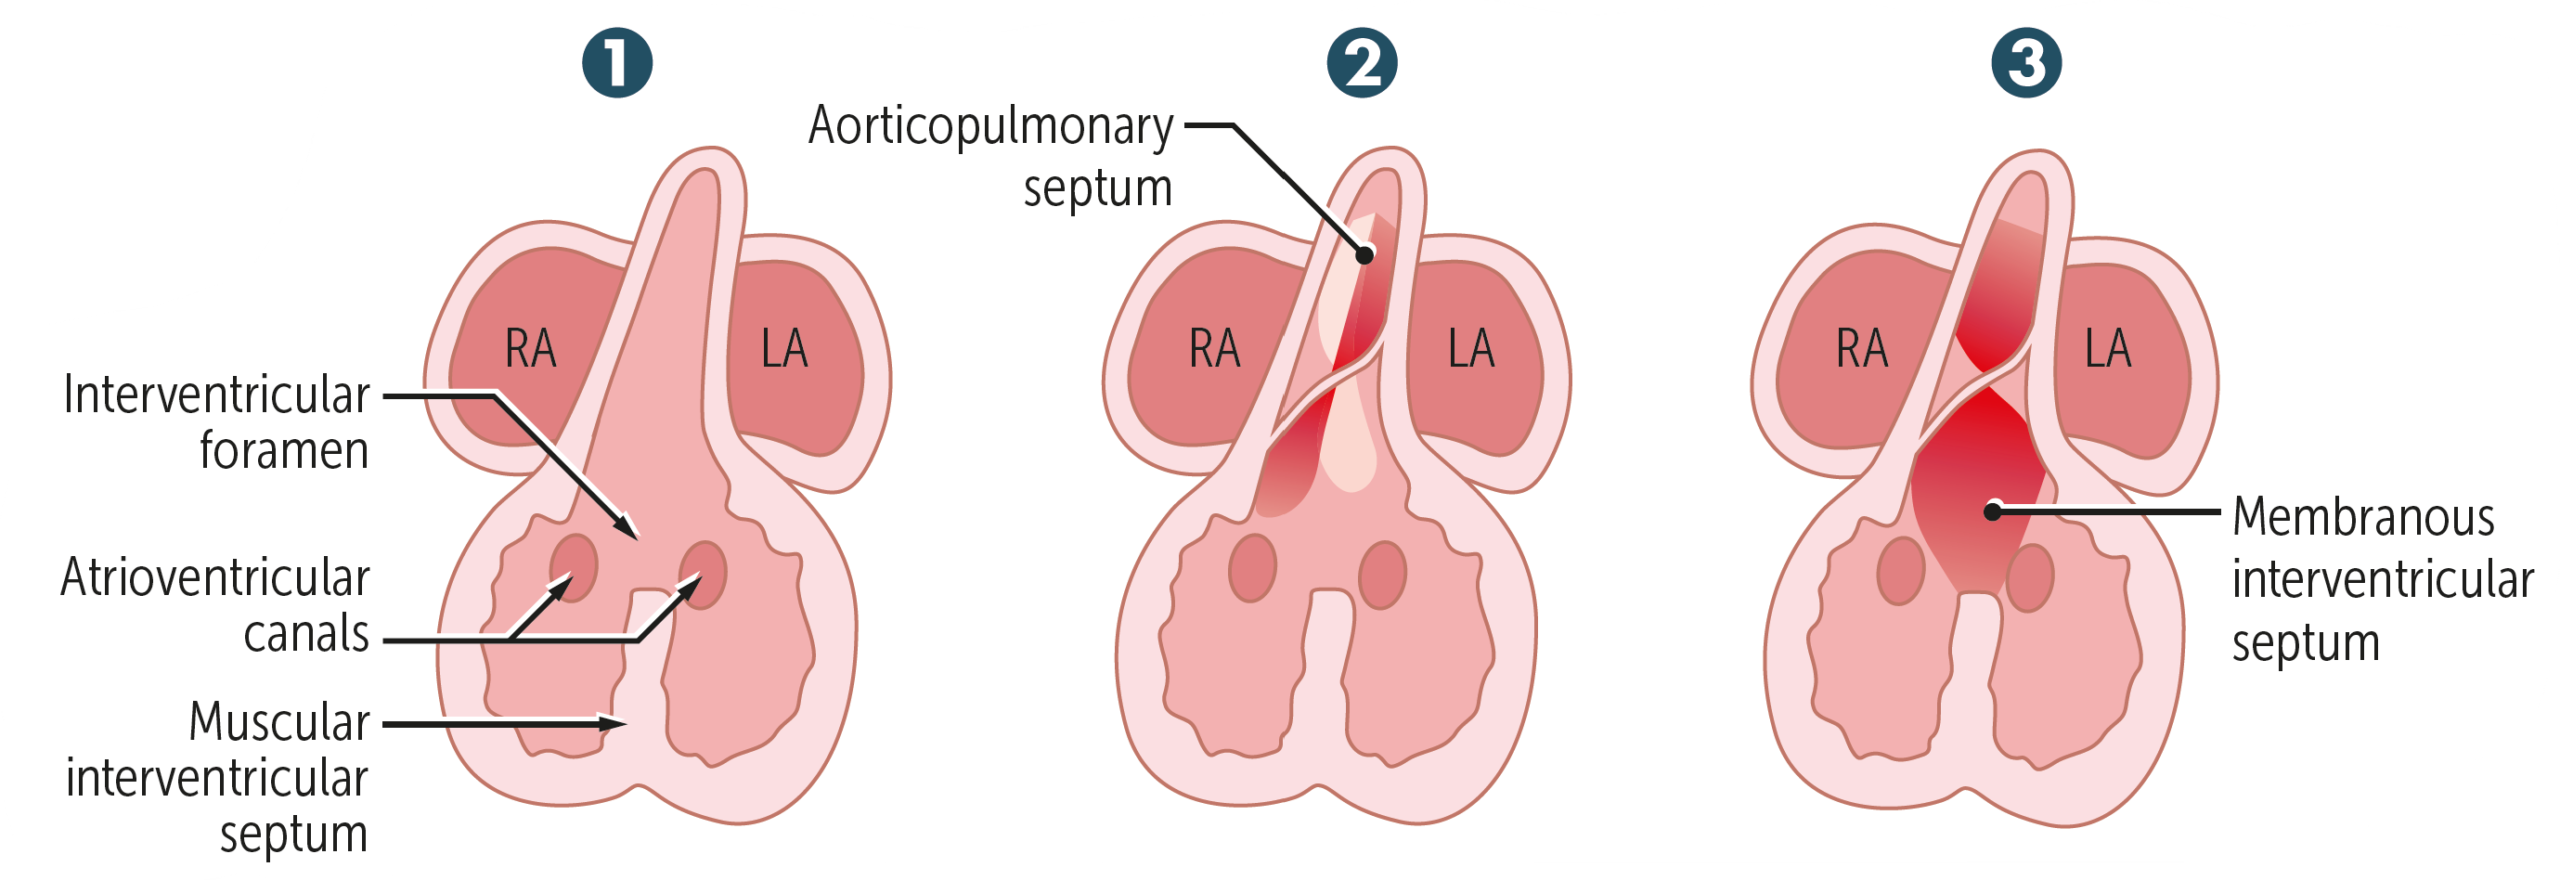
| Muscular Interventricular Septum | Grows upward from the floor of the ventricles, leaving a temporary interventricular foramen. | Muscular VSD |
| Membranous Interventricular Septum | Formed by the fusion of the aorticopulmonary septum, endocardial cushions, and muscular interventricular septum, closing the interventricular foramen. | Ventricular Septal Defect (VSD): Most common congenital cardiac anomaly, usually in the membranous septum. |
| Endocardial Cushions | Contribute to separating atria from ventricles and participate in both atrial septation and the membranous VSD region. | Atrioventricular Septal Defect (AVSD / Endocardial Cushion Defect): Single common AV valve + ASD/VSD. Associated with Down syndrome, maternal diabetes, and obesity. |
Outflow Tract Formation & Valve Development
| Structure | Embryological Origin & Mechanism | Conotruncal & Valvular Anomalies |
|---|---|---|
| Aorticopulmonary Septum | Neural crest cells migrate to form truncal and bulbar ridges that spiral and fuse, creating the ascending aorta and pulmonary trunk. | Failure of neural crest migration causes conotruncal abnormalities: • Transposition of the Great Arteries (TGA) • Tetralogy of Fallot • Persistent Truncus Arteriosus |
| Heart Valves | • Aortic/Pulmonary: Derived from outflow tract endocardial cushions. • Mitral/Tricuspid: Derived from fused AV canal endocardial cushions. |
Valvular anomalies may be stenotic, regurgitant, atretic (e.g., tricuspid atresia), or displaced (e.g., Ebstein anomaly). |
Clinical Integration & Board Exam Pearls:
- Neural Crest Derivatives: Remember that conotruncal cardiac anomalies (TGA, Tetralogy of Fallot, Truncus Arteriosus) stem from defective neural crest cell migration.
- Down Syndrome Association: Endocardial cushion defects (AVSD) are classic board associations with trisomy 21 (Down syndrome).
Key Points & Memory Hooks:
- Core Timeline: The heart begins beating in week 4, coinciding with cardiac looping and early septation milestones.
- Memory Hook: VSDs are most common in the membranous septum because closing that final hole requires the complex convergence of three distinct structures (muscular septum, endocardial cushions, and AP septum).
You must be logged in to post a comment.