
Learning Objectives
- Describe the anatomical location, size, and bony relationships of the pituitary gland within the sella turcica.
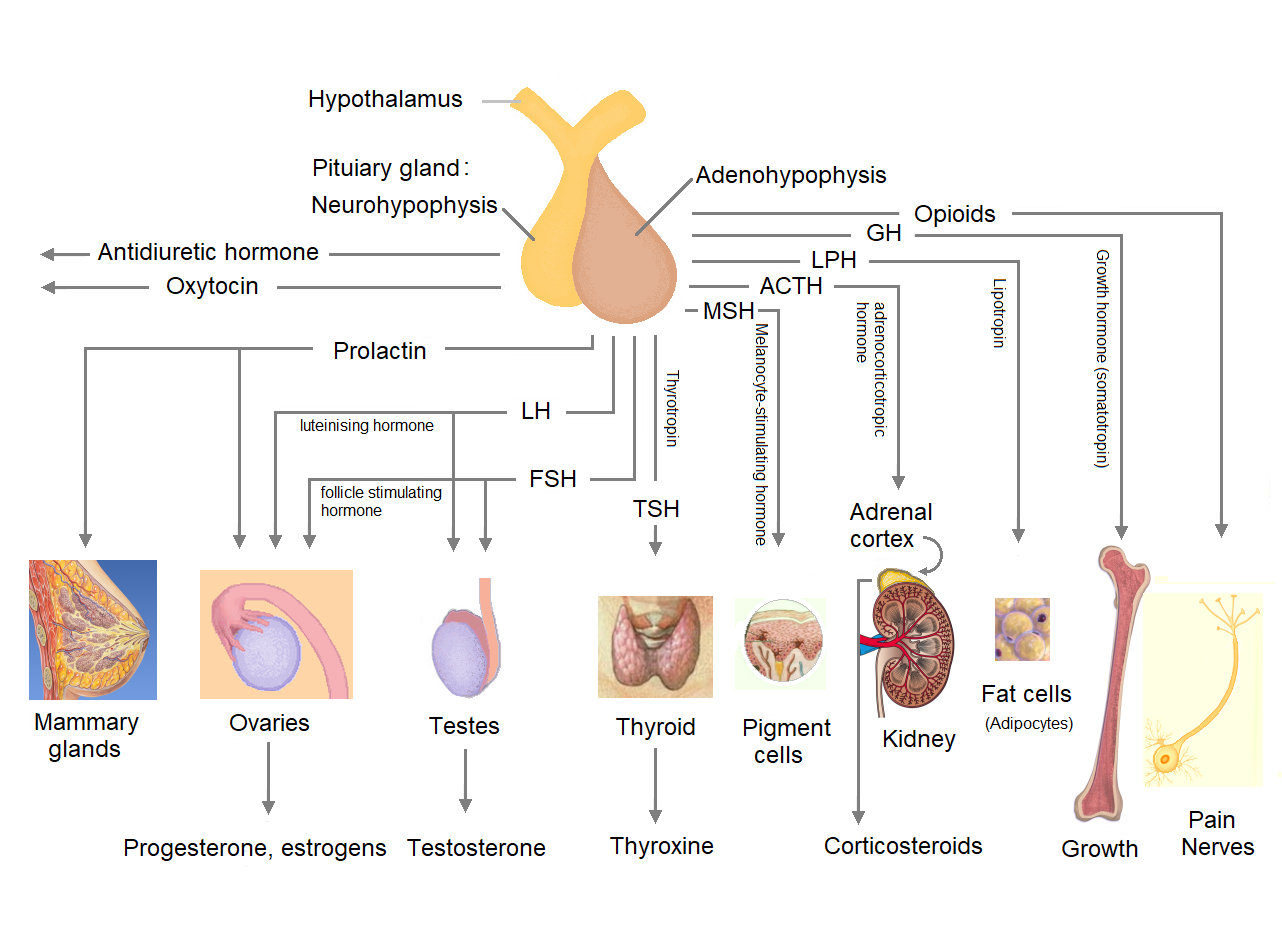
- Distinguish between the histological features and hormonal functions of the anterior pituitary (adenohypophysis) and posterior pituitary (neurohypophysis).
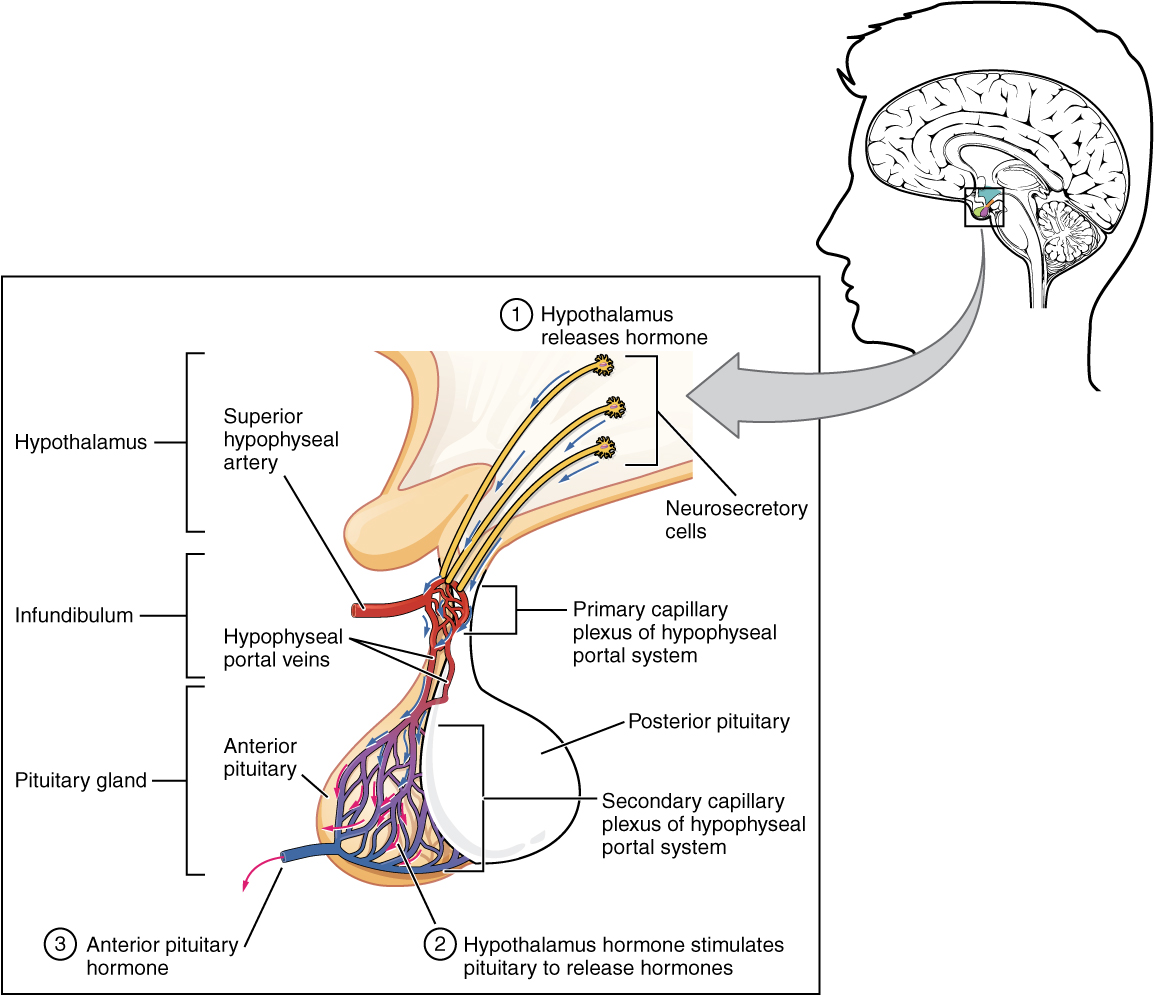
- Detail the vascular supply of the gland, highlighting the hypophyseal portal system and superior/inferior hypophyseal arteries.
- Examine clinical correlates including pituitary adenomas, diabetes insipidus, pituitary apoplexy, and transsphenoidal surgical management.
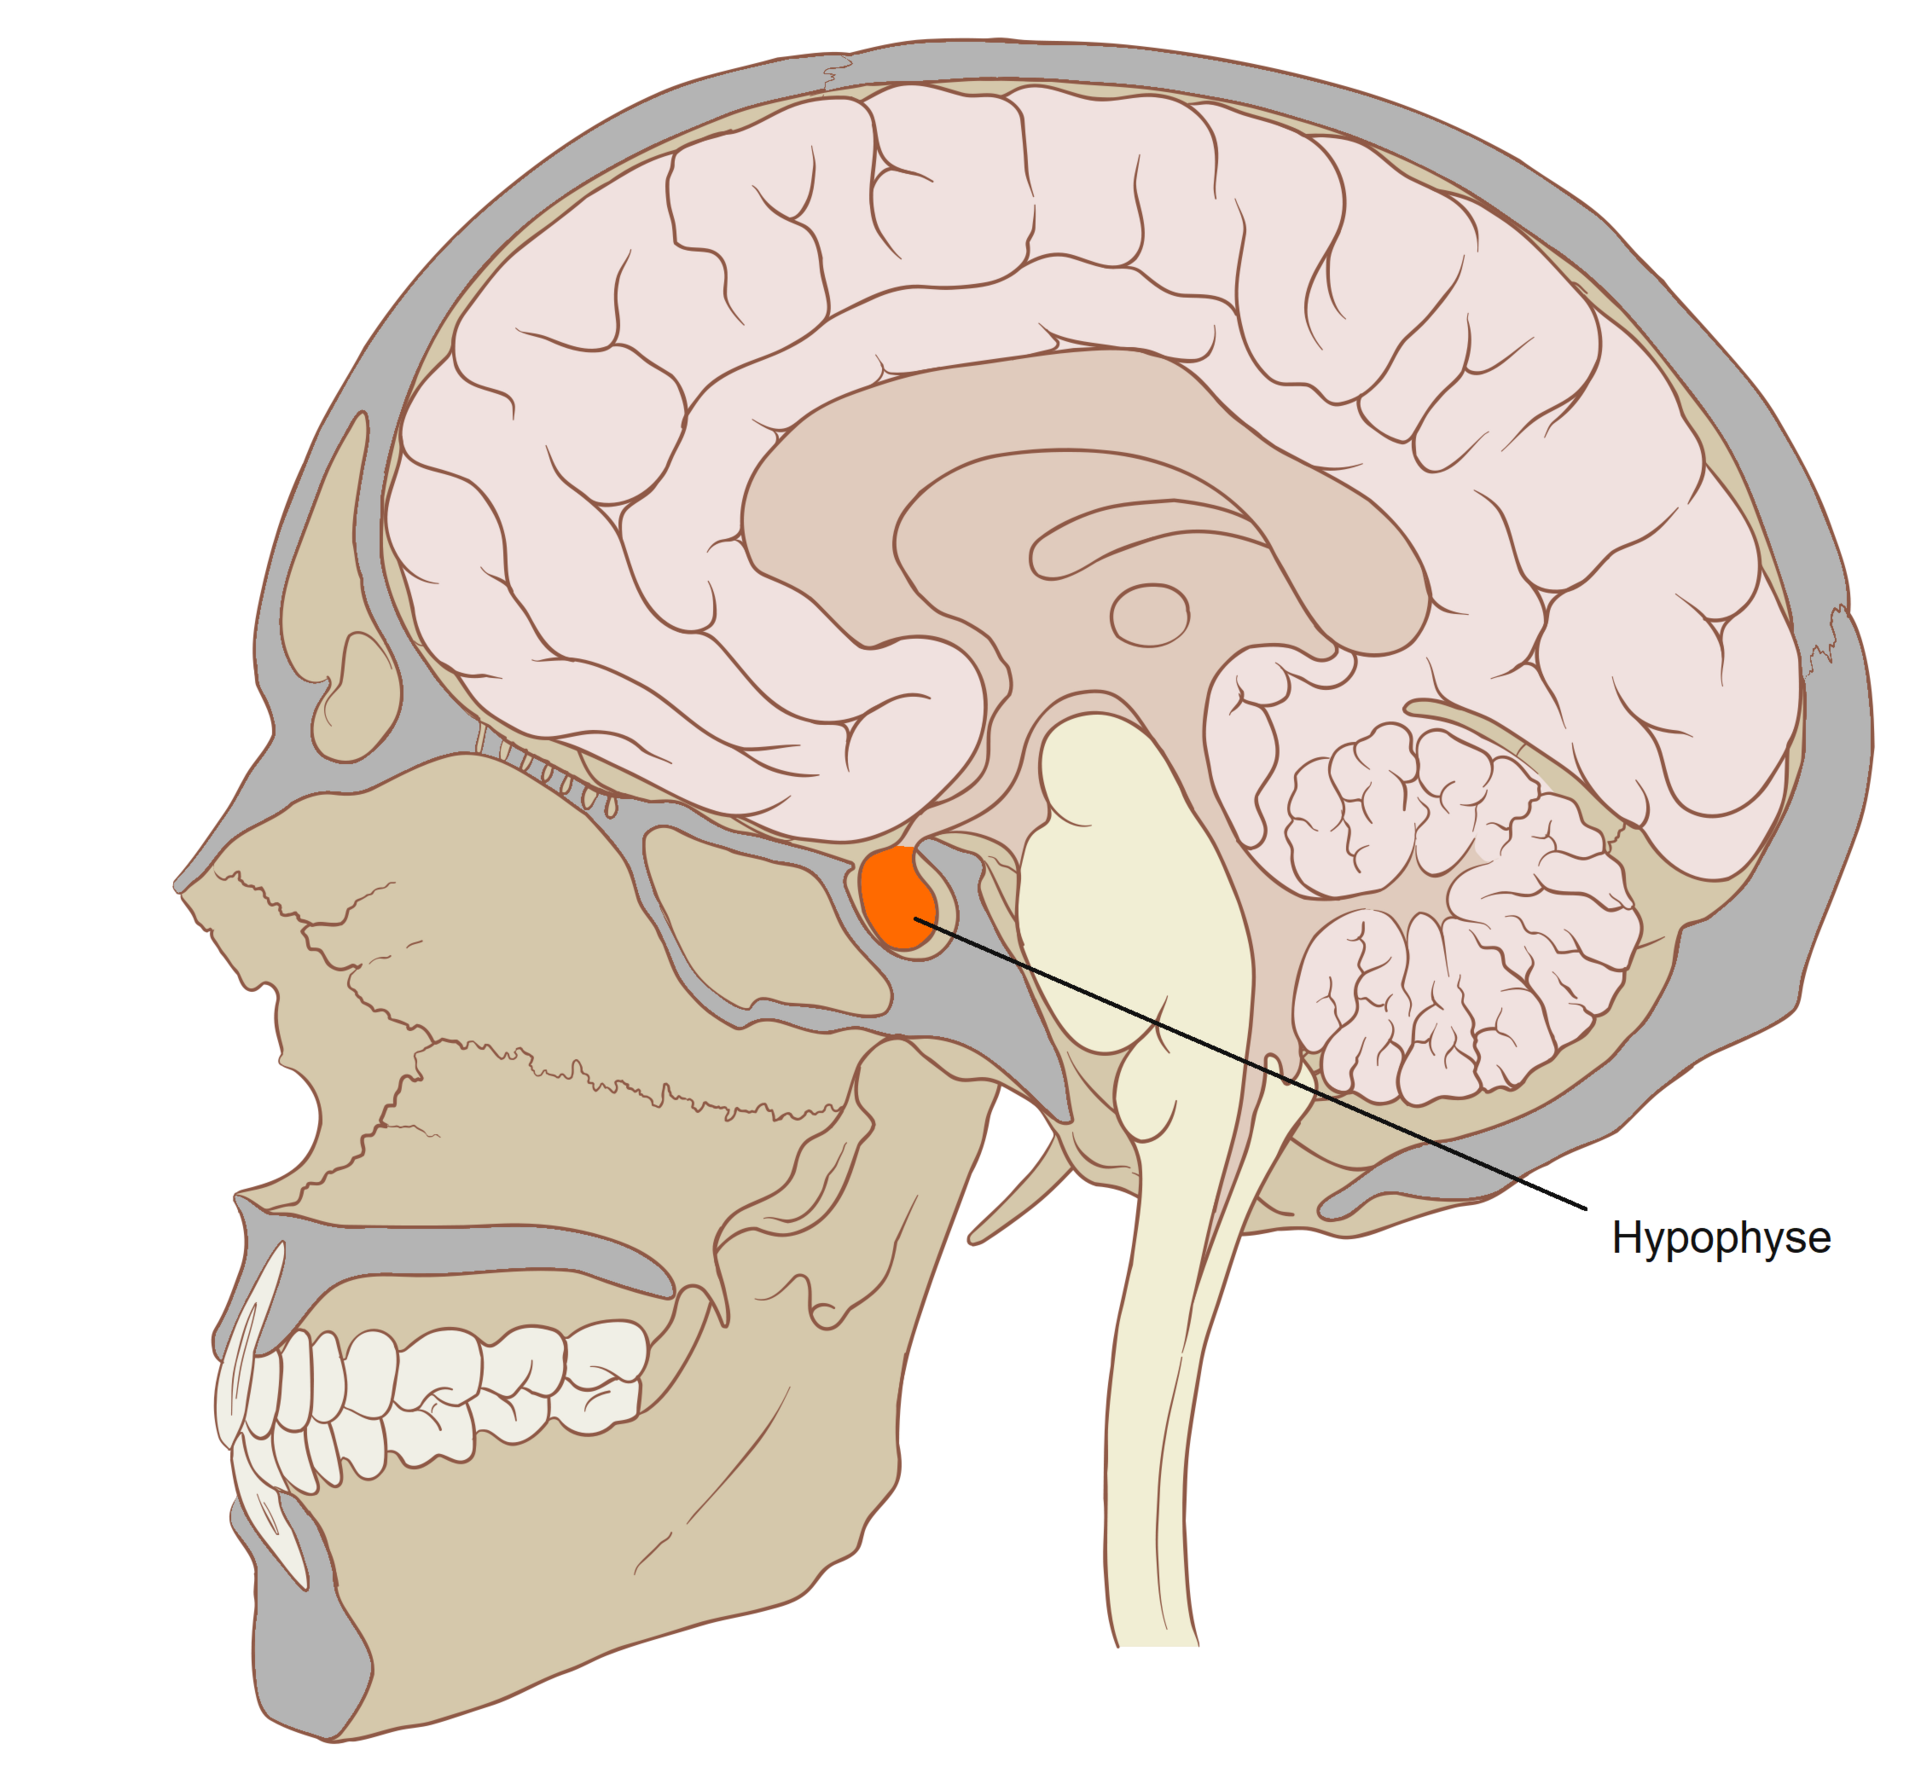
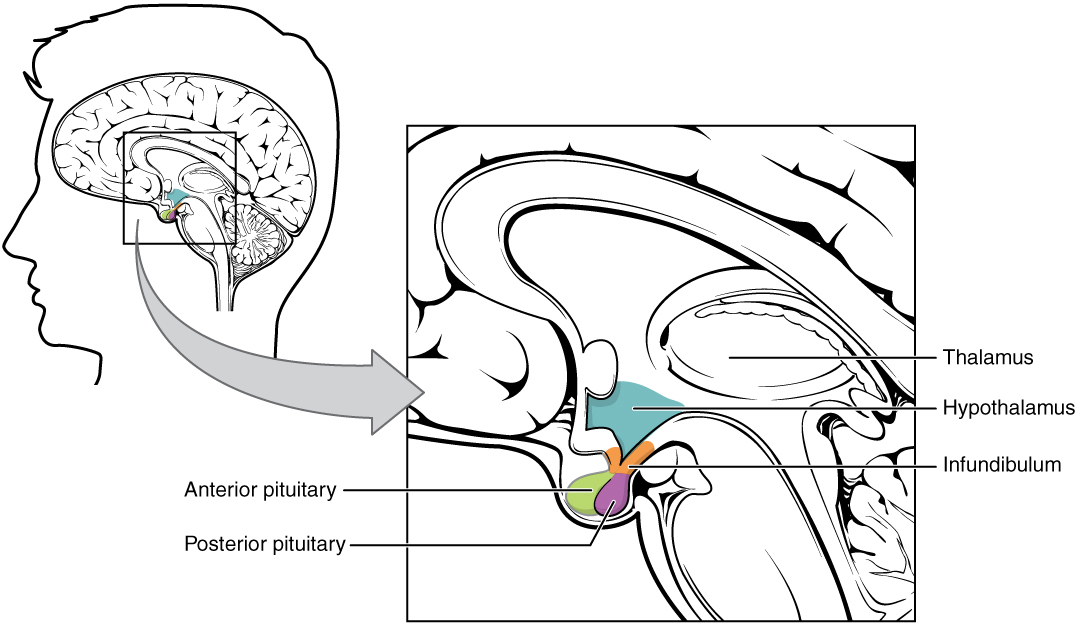
1. Anatomy & Histological Divisions
The pituitary gland (hypophysis) is an approximately 1 cm, rounded endocrine gland resting securely at the base of the brain.
| Division | Anatomical & Bony Location | Histology & Secretions |
|---|---|---|
| Anterior Pituitary (Adenohypophysis) | Housed within the sella turcica of the sphenoid bone, immediately inferior to the hypothalamus. | Composed of secretory cells: acidophils (GH, prolactin), basophils (ACTH, TSH, FSH, LH), and chromophobes. |
| Posterior Pituitary (Neurohypophysis) | Consists primarily of unmyelinated nerve fibers and supporting glial-like cells called pituicytes. |
2. Blood Supply & Portal System
- Superior Hypophyseal Arteries: Branches of the internal carotid arteries supplying the median eminence, infundibulum, and anterior pituitary.
- Inferior Hypophyseal Arteries: Supply the posterior pituitary gland.
- Hypophyseal Portal System: A specialized vascular network transferring hypothalamic releasing and inhibiting hormones directly to the adenohypophysis.
Clinical Notes & Pathology:
- Pituitary Adenomas: Common benign neoplasms causing hormone hypersecretion (e.g., Cushing’s disease, hyperprolactinemia) or mass effect (compression of the optic chiasm leading to bitemporal hemianopia).
- Diabetes Insipidus: Posterior pituitary dysfunction causing polyuria and polydipsia due to insufficient ADH production or release.
- Pituitary Apoplexy: An acute, life-threatening hemorrhagic infarction into a pituitary tumor, presenting with sudden severe headache, visual loss, and shock.
- Transsphenoidal Surgery: A surgical approach through the sphenoid sinus to resect adenomas and relieve intracranial pressure.
Key Points & Memory Hooks:
Sella Anchor: The pituitary sits snugly in the “Turkish saddle” (sella turcica) of the sphenoid bone.
Portal Precision: Hypothalamic signals travel directly to the front-lobe adenohypophysis via a robust portal capillary network.
Optic Vulnerability: Expanding pituitary masses grow upward to crush the optic chiasm, producing classic vision loss.
Sella Anchor: The pituitary sits snugly in the “Turkish saddle” (sella turcica) of the sphenoid bone.
Portal Precision: Hypothalamic signals travel directly to the front-lobe adenohypophysis via a robust portal capillary network.
Optic Vulnerability: Expanding pituitary masses grow upward to crush the optic chiasm, producing classic vision loss.
You must be logged in to post a comment.